💡 Direct Answer & Executive Summary (Autosomal Genotype Cross Probability Solver)
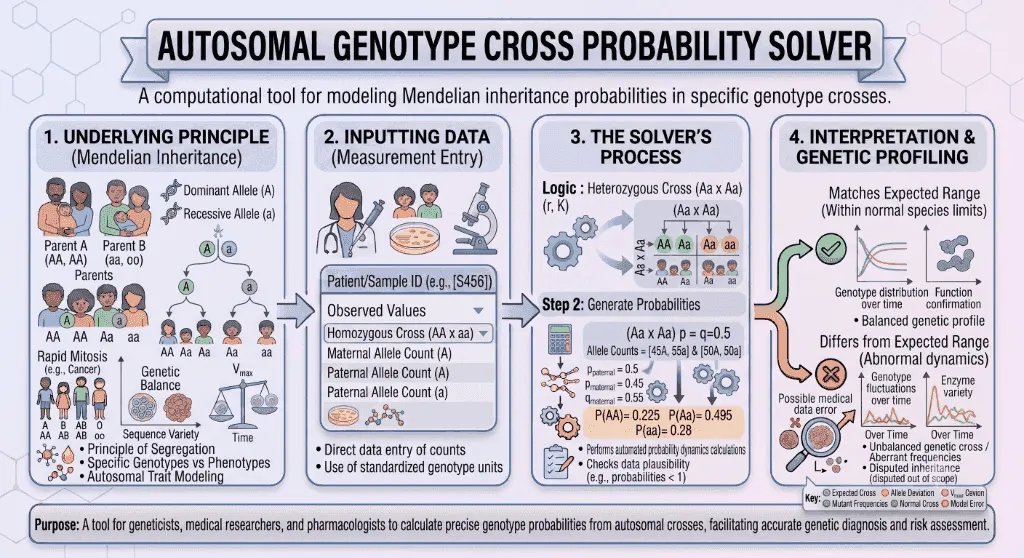
Definition: Calculate Mendelian genotype probabilities (AA, Aa, aa), phenotypic ratios, carrier recurrence risks, and clinical penetrance for autosomal recessive and dominant inheritance crosses.
Governing Math Formula: Mendel's First Law: P(AA) = pm × pp, P(Aa) = (pm × qp) + (qm × pp), P(aa) = qm × qp. For monohybrid carrier cross (Aa × Aa): 25% AA, 50% Aa, 25% aa. Healthy sibling carrier risk = 2/3 (66.7%).
Target Applications: Provides real-time quantitative solutions in Biology for students, engineers, researchers, and finance professionals.
Autosomal Genotype Cross Probability Solver: Mendelian Punnett Squares & Carrier Risk Guide
1. Introduction
In medical genetics, reproductive medicine, evolutionary biology, and molecular agriculture, predicting how hereditary traits pass from parents to offspring is rooted in Mendelian Inheritance. Whether calculating the recurrence risk of a severe genetic condition in prenatal counseling or breeding disease-resistant crops, understanding the exact probability distribution of autosomal genotypes ($AA, Aa, aa$) is essential.
Gregor Mendel’s discovery of the Law of Segregation in 1865 demonstrated that diploid organisms carry two copies of each autosomal gene (alleles), which separate equally into haploid gametes during meiosis.
For monogenic traits on non-sex chromosomes (autosomes), the interaction between dominant () and recessive () alleles creates distinct mathematical ratios. When two asymptomatic heterozygous carriers of an autosomal recessive disorder (such as Cystic Fibrosis, Sickle Cell Anemia, or Tay-Sachs disease) conceive, each pregnancy carries an independent of having an affected child (), a of producing an asymptomatic carrier (), and a of producing a homozygous wild-type child (). Furthermore, among clinically healthy living children in such families, the probability of being a carrier is .
Conversely, in autosomal dominant disorders (such as Huntington Disease, Marfan Syndrome, or Achondroplasia), a single mutant allele from an affected heterozygous parent () confers a to every offspring, regardless of biological sex.
How do maternal () and paternal () allele frequencies combine in a Punnett grid? How does incomplete clinical penetrance alter actual phenotypic disease expression?
This comprehensive guide details the mathematical equations, Punnett square logic, Bayesian pedigree adjustments, and clinical genetic counseling case studies governing autosomal genotype crosses.
flowchart LR
    PARENTS["👫 Parental Genotypes
Maternal (pm, qm) & Paternal (pp, qp)
Meiotic Segregation into Gametes"] --> PUNNETT["🧮 Punnett Cross Solver
Genotypes: P(AA), P(Aa), P(aa)
Phenotypic Ratios & Carrier Odds"]
    PUNNETT --> PENETRANCE["🔍 Clinical Penetrance & Risk
Adjust for Expressivity & Age of Onset
Healthy Sibling 2/3 Carrier Rule"]
    PENETRANCE --> ACTION["🩺 Reproductive Decision Making
Pre-implantation Genetic Testing (PGT-M) & Counseling"]
2. Definitions
2.1 Simple Everyday Definition
An Autosomal Genotype Cross Solver is a genetic probability tool that calculates the exact percentage chance that a child will inherit specific gene combinations (like healthy, carrier, or affected) from their parents based on standard Mendelian laws.
2.2 Formal Technical Definition
The Autosomal Genotype Cross Model applies Mendel's First Law of Segregation to calculate the joint probability distribution of offspring diploid genotypes from maternal allele probabilities () and paternal allele probabilities (), where :
Where:
- is the Dominant (or Wild-Type) Allele.
- is the Recessive (or Mutant) Allele.
- is Homozygous Dominant.
- is Heterozygous (Carrier in Recessive Disorders / Affected in Dominant Disorders).
- is Homozygous Recessive (Affected in Recessive Disorders / Wild-Type in Dominant Disorders).
- The Conditional Carrier Rule (): In an autosomal recessive carrier mating (), if an offspring is known to be clinically healthy (not ), the conditional probability that they are an asymptomatic carrier () is:
2.3 Vivid Real-World Analogies
The Coin Toss Pairing:
Imagine a father and mother each flipping a coin that has '' on one side and '' on the other.
- Both heads (): 25% chance.
- One heads, one tails ( or ): 50% chance.
- Both tails (): 25% chance.
Every pregnancy is a brand-new coin toss; prior children have zero influence on future coin flips.
The Backup Generator (Autosomal Recessive):
A cell requires a vital enzyme to function. Allele '' is a fully functional generator producing 100% power; allele '' is a broken generator. If a child has , they have two working generators. If they have (carrier), one generator runs at 50% capacity—which is plenty to keep all lights on (asymptomatic). Only if they inherit (two broken generators) does the power go out (clinical disease).
3. History & Scientific Milestones
The discovery of Mendelian transmission transformed biology from qualitative observation into an exact mathematical science.
flowchart TD
    M1["📅 1865: Gregor Johann Mendel
Discovers the Law of Segregation & Law of Independent Assortment in Pisum sativum"] --> M2["📅 1902: Sir Archibald Garrod
Discovers the first human autosomal recessive disease (Alkaptonuria) & 'Inborn Errors of Metabolism'"]
    M2 --> M3["📅 1905: Reginald C. Punnett
Invents the visual Punnett Square grid to model genetic crosses"]
    M3 --> M4["📅 1910: Thomas Hunt Morgan
Proves genes reside on physical chromosomes via Drosophila melanogaster genetics"]
    M4 --> M5["📅 1990s–Present: Molecular PGT-M
Pre-implantation genetic testing allows single-cell PCR diagnosis of Mendelian embryos"]- Gregor Johann Mendel (1865): Conducted hybridization experiments on $29,000$ pea plants (Pisum sativum), proving that hereditary elements ("factors") are particulate, do not blend, and segregate cleanly into gametes with predictable $3:1$ phenotypic ratios.
- Sir Archibald Garrod (1902): Identified Alkaptonuria ("black urine disease") in children of first-cousin marriages, establishing the concept of Inborn Errors of Metabolism and proving Mendelian autosomal recessive inheritance in humans.
- Reginald C. Punnett & William Bateson (1905): Devised the Punnett Square, providing the standard visual tabular tool for predicting genotypic combinations.
- Thomas Hunt Morgan (1910): Confirmed the Chromosomal Theory of Inheritance, establishing the physical basis of gene loci and linkage on autosomes and sex chromosomes.
- Modern Clinical Genetics (1990s–Present): Introduction of Pre-implantation Genetic Testing for Monogenic Disorders (PGT-M), allowing couples carrying autosomal disease mutations to screen IVF blastocysts prior to implantation.
4. Core Concepts & Biochemical Mechanisms
graph TD
    CONCEPTS["🧬 Core Principles of Autosomal Cross Inheritance"]

    CONCEPTS --> SEGREGATION["1. Meiotic Allele Segregation
• Diploid parents (2n) produce haploid gametes (1n)
• Heterozygote (Aa) produces 50% 'A' and 50% 'a' gametes
• Random fertilization combines gametes independently"]
    CONCEPTS --> RECESSIVE["2. Autosomal Recessive Inheritance
• Disease phenotype requires homozygous mutant state (aa)
• Heterozygotes (Aa) are healthy carriers (haplosufficiency)
• Cross Aa × Aa → 25% aa (affected), 50% Aa (carrier), 25% AA"]
    CONCEPTS --> DOMINANT["3. Autosomal Dominant Inheritance
• Single mutant allele (A) causes disease phenotype (haploinsufficiency / dominant negative)
• Cross Aa × aa → 50% Aa (affected), 50% aa (normal)
• Vertical transmission pattern in every generation"]
4.1 Mendelian Cross Configurations and Probability Tables
Mendelian crosses produce distinct genotype distributions based on parental zygosity:
- Carrier Cross ():- Genotypic Ratio: $1\,AA : 2\,Aa : 1\,aa$ ().- Phenotypic Ratio (Recessive trait): .
- Dominant Testcross ():- Genotypic Ratio: $1\,Aa : 1\,aa$ ().- Phenotypic Ratio (Dominant trait): .
- Homozygous Recessive Homozygous Dominant ():- Genotypic Ratio: (All offspring are obligate carriers).
4.2 Penetrance vs. Expressivity in Clinical Genetics
- Penetrance: The percentage of individuals with a specific disease genotype who actually exhibit any clinical symptoms ().- Complete Penetrance (100%): Huntington disease (all individuals develop chorea by age ).- Incomplete / Reduced Penetrance (): Retinoblastoma (, 90% penetrance) or Hereditary Hemochromatosis (, only develop clinical iron overload).
- Variable Expressivity: The degree or severity with which a genotype manifests across different individuals (e.g., Marfan syndrome can range from mild joint hypermobility to life-threatening aortic dissection within the same pedigree).
5. Formulas & Mathematical Derivations
5.1 The General Punnett Probability Formulas
Given maternal allele frequencies and paternal allele frequencies :
5.2 Autosomal Recessive Disease & Carrier Risk
For a carrier couple (, where and ):
Conditional Carrier Risk for a Healthy Sibling:
5.3 Autosomal Dominant Disease Risk
For an affected heterozygous parent and an unaffected parent (, where and ):
Adjusted Clinical Risk with Incomplete Penetrance ():
5.4 Variable Reference Table
| Parameter | Symbol | Range | Clinical Genetic Role |
|---|---|---|---|
| Maternal Dominant Allele | Probability of mother passing allele | ||
| Maternal Recessive Allele | Probability of mother passing allele () | ||
| Paternal Dominant Allele | Probability of father passing allele | ||
| Paternal Recessive Allele | Probability of father passing allele () | ||
| Homozygous Dominant | $P(AA)$ | Probability of inheriting two alleles | |
| Heterozygous (Carrier) | $P(Aa)$ | Probability of inheriting one and one allele | |
| Homozygous Recessive | $P(aa)$ | Probability of inheriting two alleles | |
| Penetrance | () | Likelihood of genotype expressing clinical symptoms |
6. Step-by-Step Computational Walkthrough
Let us evaluate the reproductive risk for a couple undergoing preconception genetic screening for Cystic Fibrosis ():
- Both the mother and father are confirmed heterozygous carriers:
- Maternal frequencies:
- Paternal frequencies:
- Clinical Penetrance:
flowchart TD
    STEP1["Step 1: Calculate Homozygous Dominant P(AA)
P(AA) = pm × pp = 0.50 × 0.50 = 0.25 (25.0% Non-carrier)"] --> STEP2["Step 2: Calculate Heterozygous Carrier P(Aa)
P(Aa) = (pm × qp) + (qm × pp) = (0.50 × 0.50) + (0.50 × 0.50) = 0.50 (50.0% Carrier)"]
    STEP2 --> STEP3["Step 3: Calculate Homozygous Recessive P(aa)
P(aa) = qm × qp = 0.50 × 0.50 = 0.25 (25.0% Affected with CF)"]
    STEP3 --> STEP4["Step 4: Determine Overall Clinical Disease Risk
P(Clinical CF) = P(aa) × Penetrance = 0.25 × 1.00 = 25.0%"]
    STEP4 --> STEP5["Step 5: Calculate Healthy Sibling Carrier Probability
P(Aa | Healthy) = 0.50 / (0.25 + 0.50) = 0.50 / 0.75 = 2/3 (66.67%)"]- Step 1: Probability of Homozygous Normal ():
- Step 2: Probability of Heterozygous Carrier ():
- Step 3: Probability of Homozygous Recessive Affected ():
- Step 4: Clinical Disease Risk to Fetus:
- Step 5: Healthy Offspring Carrier Risk ():
7. Visual Explanations & Inheritance Spectra
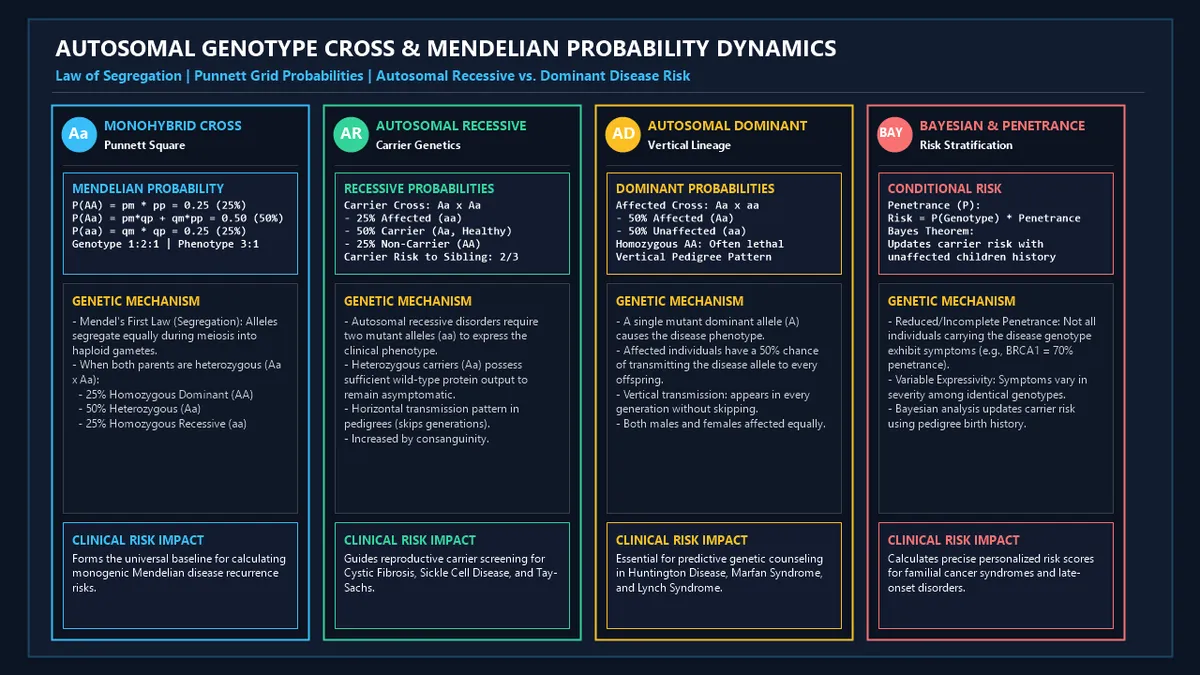
flowchart TD
    PEDIGREE["Autosomal Inheritance Patterns in Clinical Pedigrees"]

    PEDIGREE --> AR["🔵 Autosomal Recessive Pattern (e.g., Cystic Fibrosis, Sickle Cell)
• Horizontal transmission: Skips generations; appears in sibling clusters
• Equal male and female affection frequency
• Both parents of affected child are obligate carriers (Aa)
• Consanguinity significantly increases recurrence risk"]

    PEDIGREE --> AD["🟠 Autosomal Dominant Pattern (e.g., Huntington Disease, Marfan)
• Vertical transmission: Appears in every successive generation
• Every affected child has at least one affected parent (unless de novo)
• 50% transmission risk per pregnancy from heterozygous parent (Aa)
• Homozygous dominant (AA) often causes severe embryonic lethality"]
8. Comparative & Standards Tables
8.1 Mendelian Mating Genotype Distributions
| Parental Cross | Maternal | Paternal | $P(AA)$ | $P(Aa)$ | $P(aa)$ | Recessive Phenotype () | Dominant Phenotype () |
|---|---|---|---|---|---|---|---|
| Carrier Carrier | 25% | 50% | 25% | 25% Affected | 75% Dominant | ||
| Dominant Testcross | 0% | 50% | 50% | 50% Normal | 50% Affected | ||
| Homozygous Cross | 0% | 100% | 0% | 0% Affected (100% Carrier) | 100% Dominant | ||
| Affected Carrier | 0% | 50% | 50% | 50% Affected | 50% Dominant | ||
| Normal Carrier | 50% | 50% | 0% | 0% Affected (50% Carrier) | 100% Dominant | ||
| Wildtype Wildtype | 100% | 0% | 0% | 0% Affected | 100% Dominant |
8.2 Common Autosomal Genetic Disorders
| Condition | Gene Locus | Inheritance Mode | Carrier Frequency | Key Clinical Features |
|---|---|---|---|---|
| Cystic Fibrosis | CFTR () | Autosomal Recessive | (Caucasians) | Thick pulmonary mucus, pancreatic insufficiency, male infertility |
| Sickle Cell Anemia | HBB () | Autosomal Recessive | (African ancestry) | Vaso-occlusive pain crises, hemolytic anemia, splenic infarction |
| Tay-Sachs Disease | HEXA () | Autosomal Recessive | (Ashkenazi Jewish) | GM2 ganglioside accumulation, neurodegeneration, cherry-red macula |
| Phenylketonuria (PKU) | PAH () | Autosomal Recessive | Phenylalanine accumulation, intellectual disability if untreated | |
| Huntington Disease | HTT () | Autosomal Dominant | Progressive chorea, dementia, CAG trinucleotide expansion () | |
| Marfan Syndrome | FBN1 () | Autosomal Dominant | Fibrillin-1 defect, aortic root aneurysm, ectopia lentis, tall stature | |
| Achondroplasia | FGFR3 () | Autosomal Dominant | Rhizomelic dwarfism (80% de novo mutations, is lethal) |
9. Practical Real-World Applications
Example 1: Preconception Carrier Screening & In Vitro Fertilization (IVF / PGT-M)
Couples who discover both partners are carriers for Spinal Muscular Atrophy (SMN1) or Cystic Fibrosis (CFTR) utilize PGT-M. Biopsied blastocyst cells undergo PCR testing to select only (normal) or (carrier) embryos for uterine transfer, eliminating the 25% disease risk.
Example 2: Predictive Testing for Late-Onset Autosomal Dominant Disorders
An adult whose parent died of Huntington Disease faces an a priori of having inherited the mutant allele. Genetic counselors provide pre-test psychological counseling before sequencing the HTT CAG repeat length.
Example 3: Mandatory Universal Newborn Bloodspot Screening
All newborns in modern hospitals undergo heel-prick blood screening for autosomal recessive metabolic disorders (PKU, Galactosemia, Medium-Chain Acyl-CoA Dehydrogenase Deficiency), initiating dietary therapy before irreversible neurodevelopmental injury occurs.
10. In-Depth Case Studies
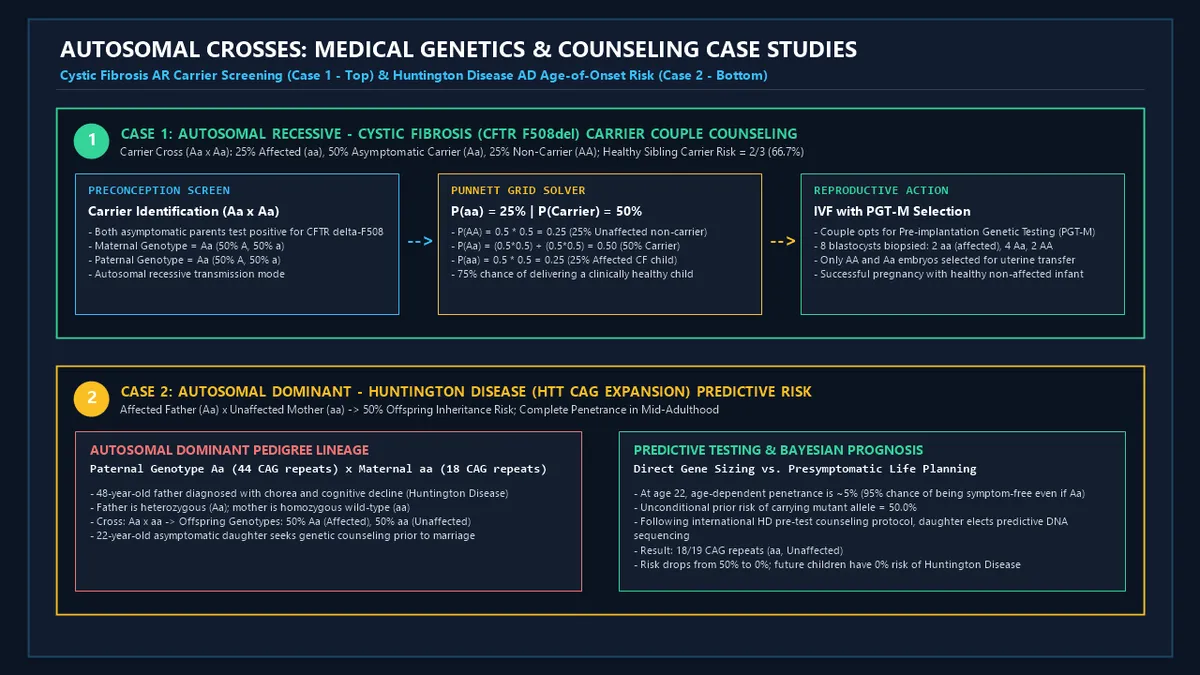
Case Study 1: Autosomal Recessive — Cystic Fibrosis () Carrier Couple Counseling
- Clinical Scenario: A woman and her husband undergo expanded preconception carrier screening. Both test positive for the classic mutation in the CFTR gene. Neither partner has any symptoms of cystic fibrosis.
- Genetic Cross Formulation:- Maternal Genotype: (Heterozygous Carrier)- Paternal Genotype: (Heterozygous Carrier)
- Offspring Probability Breakdown:
- Clinical Counseling Strategy: The genetic counselor explains that they have a of having a clinically healthy child in any given pregnancy. The couple elects to proceed with IVF combined with PGT-M. Of eight biopsied embryos, two are (affected), four are (carriers), and two are (non-carriers). An embryo is transferred, resulting in the birth of a healthy child free of CF mutations.
Case Study 2: Autosomal Dominant — Huntington Disease ( Expansion) Predictive Risk
- Clinical Scenario: A father is clinically diagnosed with Huntington Disease, confirmed by genetic testing showing in the HTT gene (Genotype ). His daughter (currently asymptomatic) seeks genetic counseling prior to starting a family.
- Mendelian Cross Setup:- Affected Father: (Heterozygous)- Unaffected Mother: (Homozygous Wild-Type)
- A Priori Transmission Risk:
- Age-Dependent Penetrance Consideration: At age , the age-dependent penetrance of Huntington disease is only , meaning that even if she carries the mutation, there is a 95% chance she would still be symptom-free today.
- Predictive Testing Outcome: After a standard 3-session predictive counseling protocol, the daughter elects to undergo direct genetic sequencing. Her test reveals (Genotype , completely normal). Her personal disease risk drops from 50% to 0%, and she cannot pass the mutation to any future children.
11. Advantages of Autosomal Cross Modeling
- Quantifies Exact Recurrence Risks: Provides empirical, non-biased probabilities () for prospective parents.
- Eliminates Misconceptions: Dispels the "Gambler's Fallacy" that having one affected child makes the next child guaranteed to be healthy.
- Applies the Healthy Sibling Rule: Accurately stratifies carrier risks for unaffected siblings in recessive pedigrees.
- Guides Advanced Reproductive Options: Informs decisions regarding prenatal chorionic villus sampling (CVS), amniocentesis, and IVF with PGT-M.
12. Methodological Complexities & Artifacts
- Germline Mosaicism: If a mutation occurs in a subset of parental germ cells during embryonic development, an apparently unaffected parent with normal blood DNA testing can produce multiple affected children with an autosomal dominant condition.
- De Novo Mutations: A significant fraction of dominant disorders arise as new spontaneous germline mutations (e.g., 80% of Achondroplasia and 50% of Marfan syndrome cases occur in families with no prior history).
- Non-Paternity / Misattributed Parentage: True genetic risk calculations depend strictly on biological kinship; undetected non-paternity can lead to erroneous risk assessments.
13. Common Mistakes to Avoid
1. The Gambler's Fallacy in Monogenic Recurrence Risk:
If a carrier couple () already has one child with cystic fibrosis (), the chance that their next child will have CF is still exactly 25%. Each conception is an independent statistical event.
2. Forgetting to Apply the Rule for Unaffected Siblings:
When an unaffected individual has a sibling with an autosomal recessive disease, their chance of being a carrier is not 50%, but , because the homozygous recessive genotype () is excluded from the sample space.
3. Assuming Autosomal Dominant Means More Common:
"Dominant" refers strictly to allele masking in heterozygotes, not population frequency. For example, Achondroplasia is dominant but rare ().
12. Frequently Asked Questions (FAQ)
What is the difference between an autosome and a sex chromosome?
Autosomes are the pairs of numbered chromosomes identical in males and females. Sex chromosomes ( and ) determine biological sex and follow sex-linked inheritance patterns.
If both parents are carriers of an autosomal recessive disease, what are the odds for their child?
For every pregnancy, there is a:
- 25% chance the child has the disease ().
- 50% chance the child is a healthy carrier ().
- 25% chance the child is completely unaffected and a non-carrier ().
Why is the carrier risk for a healthy sibling of an affected child?
Because the child is known to be healthy, the outcome (25%) is eliminated. The remaining possible outcomes are $1\,AA$ and $2\,Aa$ (total of equal parts). Thus, out of (66.7%) are carriers ().
What is incomplete penetrance?
Incomplete penetrance occurs when individuals carrying a disease-causing genotype do not express the clinical symptoms of the condition due to modifier genes or environmental factors.
Why are homozygous dominant () individuals rare in autosomal dominant disorders?
In many autosomal dominant diseases (e.g., Achondroplasia, Familial Hypercholesterolemia), possessing two mutant alleles () causes severe developmental defects resulting in early embryonic lethality or critical neonatal demise.
Can two unaffected parents have a child with an autosomal dominant disease?
Yes, via two primary mechanisms: 1. A de novo (new spontaneous) mutation in the egg or sperm. 2. Parental germline mosaicism or reduced penetrance.
How does consanguinity (marriage between relatives) affect autosomal crosses?
Consanguineous unions significantly increase the probability that both partners have inherited the same rare recessive mutant allele from a shared common ancestor, elevating the risk of autosomal recessive disorders in their offspring.
15. Expert Tips for Genetic Counselors, Medical Geneticists & Biologists
- Always Construct a 3-Generation Pedigree: Draw standard standardized pedigree symbols (squares for males, circles for females, darkened shapes for affected individuals) to verify the transmission pattern before running probability models.
- Utilize Bayesian Analysis for Negative Family History: In late-onset dominant conditions, systematically reduce a consultant's carrier probability as they remain healthy past the median age of symptom onset.
- Differentiate Carrier Frequency () from Disease Incidence (): When calculating population risk, remember that asymptomatic carriers () are vastly more numerous than affected individuals () for rare recessive disorders (Hardy-Weinberg Principle).
16. Summary Checklist
- ✔ Identify Parental Genotypes: Determine maternal () and paternal () allele states.
- ✔ Classify Inheritance Mode: Distinguish Autosomal Recessive vs. Autosomal Dominant.
- ✔ Calculate Punnett Genotype Frequencies: Solve $P(AA), P(Aa), P(aa)$.
- ✔ Determine Clinical Disease Risk: Adjust genotypic probability by clinical penetrance ().
- ✔ Apply the Healthy Sibling Rule: Calculate carrier probability for unaffected family members.
- ✔ Incorporate Pedigree History: Adjust probabilities for de novo mutations or germline mosaicism.
- ✔ Guide Reproductive Counseling: Provide clear, empirical risk assessments to support patient decision-making.
Additional Technical Guidelines & Measurement Standards
When conducting calculations for Autosomal Genotype Cross Probability Solver, maintaining quantitative precision and verifying input parameter boundaries is essential for reliable scenario evaluation. Always verify that raw numerical inputs are measured using standardized instrumentation, and double-check unit conversions prior to applying outputs in commercial, industrial, or academic projects.
For quantitative unit conversions and scientific calculations, always maintain at least four decimal places of precision during intermediate arithmetic stages before rounding final results. When preparing technical reports, laboratory documentation, or financial forecasts, cross-verify all output variables against established international measurement standards (such as SI, NIST, and ISO metric benchmarks) to guarantee consistent analytical rigor across all computational workflows.
MathsLover.com delivers this interactive solver 100% free of charge to foster global mathematical literacy, educational accessibility, and data-driven problem solving across scientific, technical, and academic communities worldwide.